A Strong Response Documented Across Follow-Up Scans
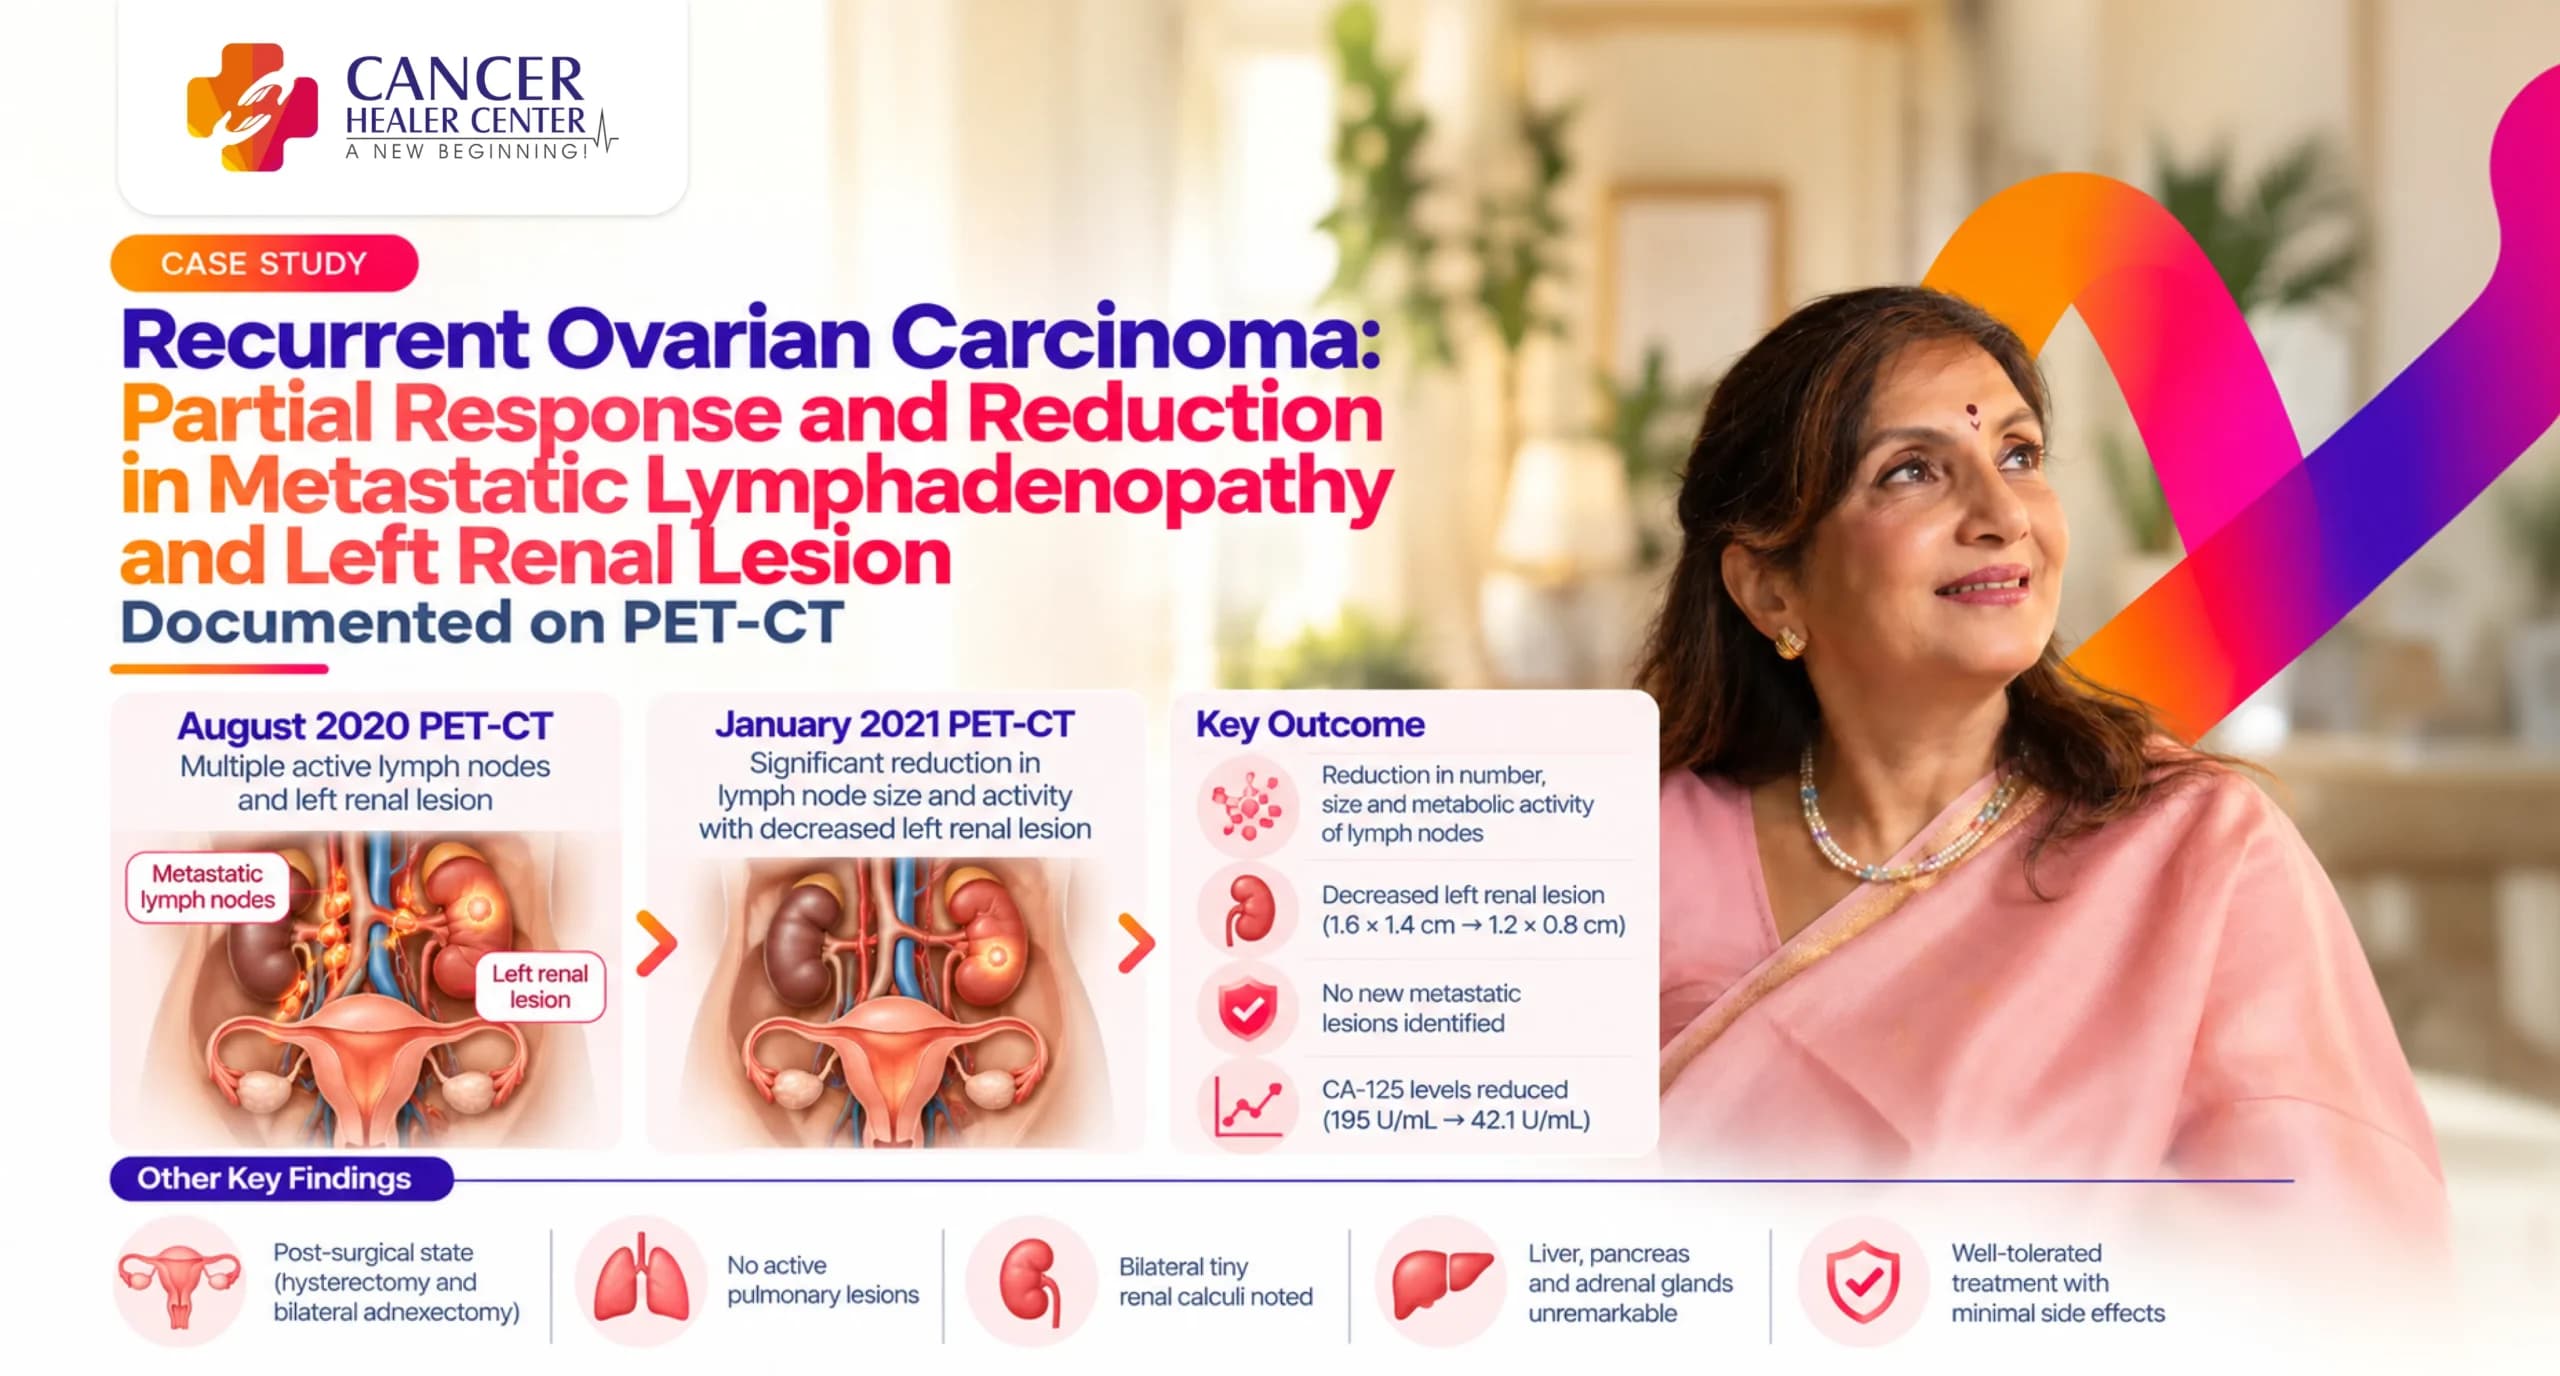
This case study documents the clinical progress and therapeutic response of a 60–61-year-old female diagnosed with recurrent ovarian carcinoma (Ca Ovary, diagnosed 2013) post-multiple lines of prior treatment. Following systemic therapy (3 cycles of Gemcitabine & Cisplatin-based chemotherapy combined with immunotherapy), sequential whole-body 18F-FDG PET-CT imaging demonstrated a significant reduction in metabolic activity, lesion size, and lymph node burden, confirming a documented partial response without new disease foci.
Neera Tripathi’s Case at a Glance
| Patient Name: | Mrs. Neera Tripathi |
| Age / Gender: | 60–61 Years / Female |
| CR No. / Order No.: | 153747 / DIRRGCI4148210 (DIRRGCI4024624) |
| Primary Diagnosis: | Recurrent Case of Ca Ovary (2013) status post-multiple lines of treatment |
| Clinical Presentation: | Rising CA-125 level (195 U/mL in Dec 2019; 42.1 U/mL post-treatment) |
| Treatment Phase: | Post 3 cycles of Gemcitabine & Cisplatin chemotherapy combined with CHC Immunotherapy |
| Primary Outcome: | Partial response with significant reduction in number, size, and metabolic SUV values of lymph nodes and left kidney lesion; no new lesions identified |
Neera Tripathi’s Treatment Journey
Mrs. Neera Tripathi was originally diagnosed with ovarian carcinoma in 2013 and underwent initial surgical resection (hysterectomy and bilateral adnexectomy) and primary therapies. In August 2020, baseline PET-CT scanning for disease progression revealed progressive hypermetabolic lymphadenopathy (supraclavicular, retrocrural, paraaortic, aortocaval) and a high-uptake left renal cortical lesion. She subsequently received 3 cycles of Gemcitabine & Cisplatin chemotherapy integrated with Cancer Healer Center (CHC) immunotherapy. Follow-up evaluation in January 2021 documented a marked reduction in hypermetabolic nodal and renal lesion burdens alongside well-tolerated treatment with minimal side effects.
What the August 2020 PET-CT Showed
A baseline whole-body 18F-FDG PET-CT scan without diagnostic CT was conducted at Rajiv Gandhi Cancer Institute and Research Centre on 31-Aug-2020 (Order Date: 31-Aug-2020).
Metabolically Active Progressive Lymphadenopathy
- Left Supraclavicular: 4.0 x 2.2 cm, SUVmax = 11.2
- Left Retrocrural: 2.6 x 1.2 cm, SUVmax = 8.4
- Paraaortic: 1.4 x 1.2 cm, SUVmax = 6.0 (closely abutting the left adrenal gland)
- Other Nodal Foci: Aortocaval and left external iliac regions
Metabolically Active Left Kidney Lesion
- Renal Cortical Lesion: 1.6 x 1.4 cm, SUVmax = 11.4 in the upper pole of the left kidney
Other Findings Identified
- Pelvic Vault: Uterus and bilateral adnexae not visualized (post-surgical state). No focal abnormal tracer uptake in the vaginal vault.
- Kidneys: Bilateral tiny renal calculi noted. Right adrenal gland was unremarkable.
- Chest & Lungs: Unremarkable; no active pulmonary nodules, infiltrates, or pleural effusions. Few subcentimeter prevascular, right lower paratracheal, and hilar lymph nodes with mild uptake were noted as inflammatory.
How the August 2020 Scan Was Interpreted
- Impression: Metabolically active progressive lymphadenopathy and left kidney lesion as described.
- Other Areas: No other metabolically active disease elsewhere in the body.
What the January 2021 PET-CT Confirmed
A follow-up whole-body 18F-FDG PET-CT scan was performed at Rajiv Gandhi Cancer Institute and Research Centre on 14-Jan-2021 (Order Date: 14-Jan-2021, Study Date: 14-Jan-2021) following 3 cycles of Gemcitabine & Cisplatin chemotherapy.
Reduction in Lymph Node Size, Number, and SUVmax
- Left Supraclavicular: Reduced in size to 3.2 x 1.6 cm and SUVmax dropped from 11.2 to 6.6.
- Left Retrocrural: Reduced in intensity with SUVmax dropping from 8.4 to 3.8.
- Paraaortic: 1.6 x 1.2 cm (inseparable from left adrenal gland) with SUVmax dropping from 6.0 to 6.6 (overall nodal count and volume reduced).
- Aortocaval: Subcentimeter region showing regression.
Reduction in Left Kidney Lesion SUVmax
- Left Renal Cortical Lesion: Size decreased to 1.2 x 0.8 cm (upper pole) and SUVmax dropped substantially from 11.4 to 6.4.
No New Lesions or Metastases
- Disease Clearance: No new abnormal tracer-avid lesions or metastatic deposits were identified anywhere across the body.
Other Areas Assessed
- CA-125 Level: CA-125 tumor marker level declined to 42.1 U/mL.
- Abdominal Viscera: Liver, spleen, gallbladder, pancreas, stomach bed, and mesentery showed normal physiological tracer distribution without active foci.
- Skeletal System: Normal physiological tracer distribution in axial and appendicular skeleton.
How the January 2021 Scan Was Interpreted
- Impression 1: Partial response to treatment with residual metabolically active lymphnodes & left kidney lesion as described.
- Impression 2: No other metabolically active disease elsewhere in the body.
The Response Documented Over Time
| [Dec 2019] CA-125 Level Measured at 195 U/mL │ ▼ [Aug 2020] Baseline PET-CT: Progressive High SUV Nodes (SUVmax up to 11.2) & Left Kidney Lesion (SUVmax 11.4) │ ▼ [Sep 2020 – Dec 2020] 3 Cycles Gemcitabine + Cisplatin & Integrated Immunotherapy │ ▼ [Jan 2021] Follow-up PET-CT: Partial Response; Significant Reduction in Nodal Size/SUV (SUVmax 6.6) & Kidney Lesion (SUVmax 6.4); CA-125 at 42.1 U/mL |
What the Two Reports Confirm
- Systemic Disease Regression: Substantial reduction in the size, number, and metabolic intensity (SUVmax) of hypermetabolic lymphadenopathy across supraclavicular, retrocrural, and retroperitoneal nodal basins.
- Organ-Specific Lesion Shrinkage: The left upper pole renal cortical lesion shrank from 1.6 x 1.4 cm (SUVmax 11.4) to 1.2 x 0.8 cm (SUVmax 6.4).
- Biochemical and Clinical Synergy: CA-125 decreased towards baseline along with clinical reporting of maintained body weight, appetite, and minimal chemotherapy toxicity during combination therapy.
Understanding the PET-CT Findings
- SUVmax Reduction: Standardized Uptake Value (SUVmax) reflects glucose utilization by cancer cells. A significant decline in SUVmax (e.g., from 11.2 to 6.6 in supraclavicular nodes and 11.4 to 6.4 in the renal lesion) demonstrates successful treatment response and decreased malignant cell viability.
- Partial Response (PR): Defined under RECIST/PERCIST criteria as a >= 30% decrease in the sum of target lesion diameters and significant reduction in metabolic radiotracer uptake without the emergence of new malignant foci.
Conclusion
The clinical case of Mrs. Neera Tripathi highlights a clear partial response and effective disease stabilization in recurrent ovarian carcinoma. Serial PET-CT monitoring from August 2020 to January 2021 provided objective imaging evidence of reduced tumor metabolic activity and anatomical shrinkage across multiple metastatic sites following combination therapy.
Every Ovarian Cancer Case Requires Individual Assessment
Disclaimer: Every oncology case presents unique clinical variables. Treatment options, diagnostic monitoring protocols, and outcomes vary based on individual staging, histological sub-types, previous treatment lines, and patient-specific factors. Consultation with a qualified oncologist is essential for personalized medical evaluation.
Medical Reports
(Diagnostic PET-CT scans from Rajiv Gandhi Cancer Institute and Research Centre, Department of Nuclear Medicine, along with patient testimonial correspondence)
Medical Reports
Frequently Asked Questions
It indicates that the existing tumor lesions and affected lymph nodes have significantly decreased in size and/or metabolic glucose uptake (SUVmax), though some residual active disease remains present.
Comparing SUVmax across serial scans allows oncologists to objectively quantify whether a tumor’s metabolic activity is increasing (progression), decreasing (treatment response), or remaining stable.
CA-125 is a serum protein biomarker commonly elevated in ovarian carcinoma. Tracking CA-125 alongside PET-CT imaging provides both biochemical and visual confirmation of disease status and treatment response.