A Strong Response Documented Across Follow-Up Scans
This case study documents the clinical progress and treatment response of a 27-year-old female diagnosed with Anaplastic Large Cell Lymphoma (ALCL) / Non-Hodgkin’s Lymphoma (NHL). Serial evaluation through PET-CT scans, magnetic resonance imaging (MRI), bone marrow biopsy, and routine blood profiling demonstrated complete metabolic resolution of active disease and overall physiological stability.
Mrs. Mansi Bhatia’s Case at a Glance
| Patient Name: | Mrs. Mansi Bhatia |
| Age / Gender: | 27 Years / Female |
| Diagnosis: | Anaplastic Large Cell Lymphoma (ALCL) / Non-Hodgkin’s Lymphoma (NHL) |
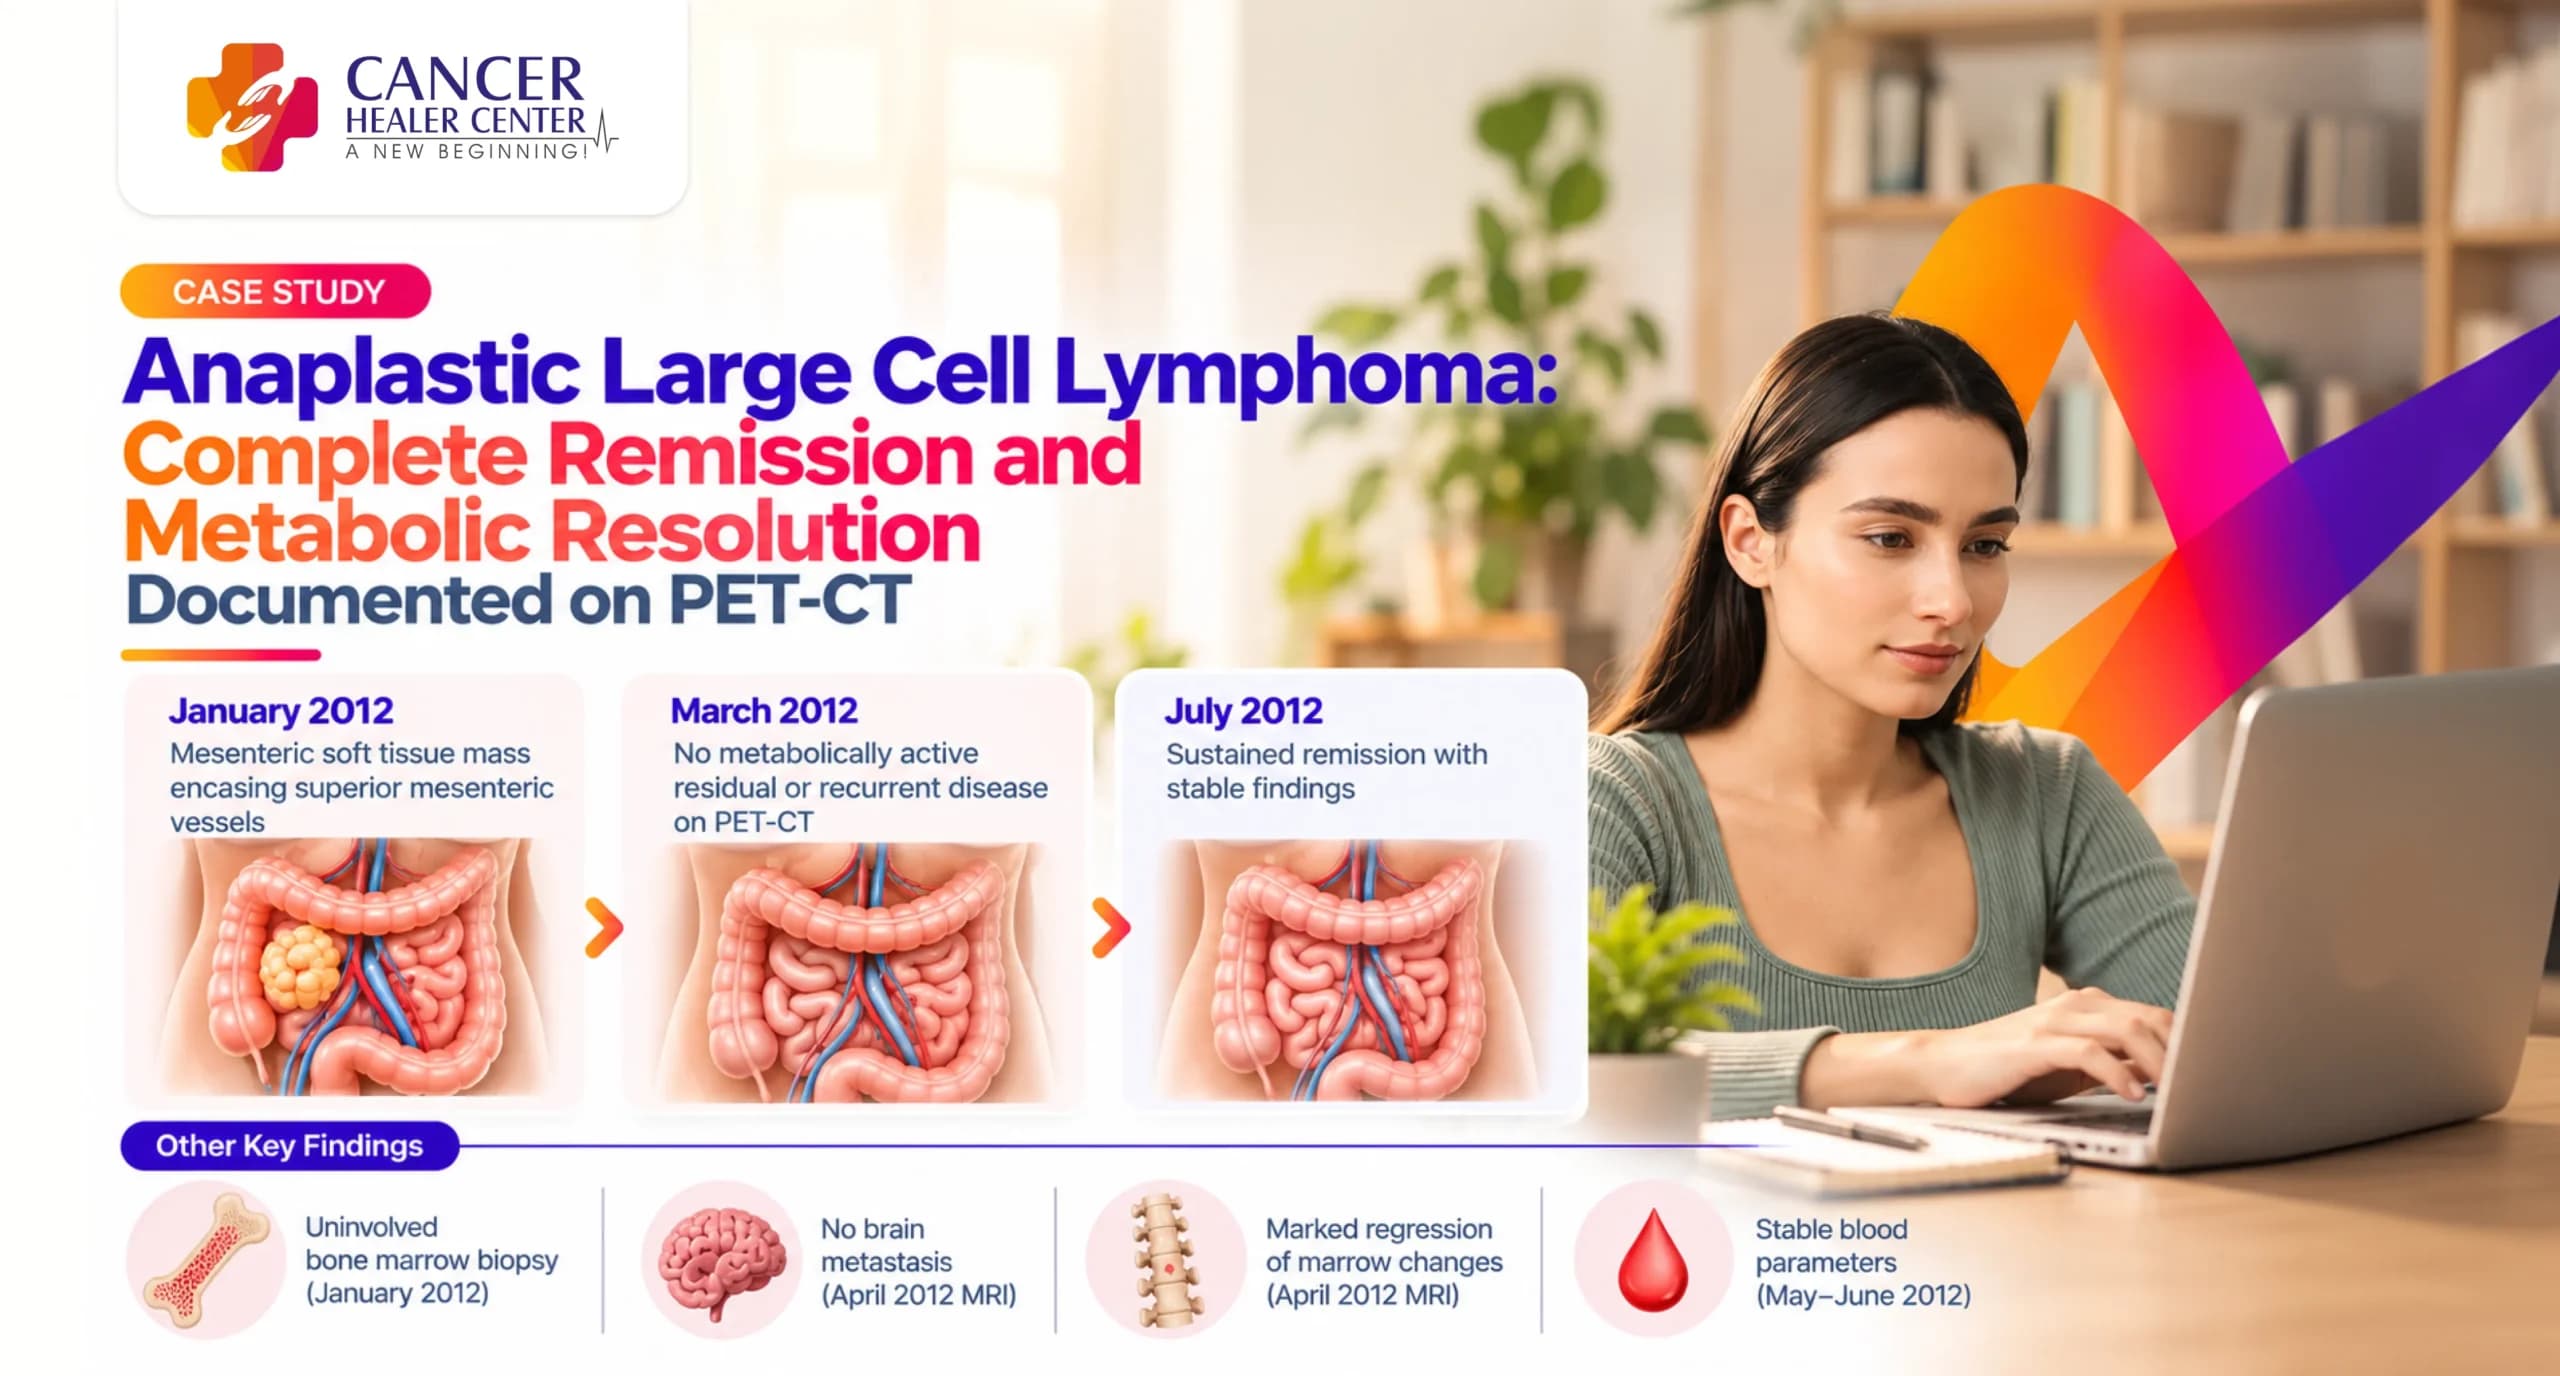
| Key Findings at Presentation: | Mesenteric soft tissue mass encasing superior mesenteric vessels |
| Treatment Phase: | Post Surgery / Radiotherapy / Chemotherapy follow-up |
| Primary Outcome: | Complete absence of metabolically active residual or recurrent lymphoma on PET-CT imaging with stable lab profiles over time |
Mrs. Mansi Bhatia’s Treatment Journey
Mrs. Mansi Bhatia presented for diagnostic evaluation and staging of Non-Hodgkin’s Lymphoma in early 2012. Following combined therapeutic interventions (including surgery, radiotherapy, and chemotherapy cycles), sequential monitoring was carried out using high-resolution PET-CT imaging, MRI, bone marrow aspirate evaluation, and comprehensive hematology/biochemistry panels to track disease response and systemic recovery.
What the Initial Diagnostic Workup Showed (January 2012)
Bone Marrow Biopsy Results
A bone marrow biopsy performed on 23-Jan-2012 (Biopsy No: B/390/2012) at Rajiv Gandhi Cancer Institute and Research Centre revealed:
- Gross Examination: Single bony core measuring 2.0 cm.
- Microscopic Examination: Hypercellular marrow with approximately 80–90% cellularity showing myeloid and megakaryocytic preponderance.
- Opinion: Uninvolved bone marrow biopsy; no unequivocal focus of Non-Hodgkin’s Lymphoma (NHL) involvement was noted.
Initial MRI Findings
An MRI review conducted on 19-Jan-2012 (Order No: DIRRGCI653771) demonstrated:
- Mesenteric Region: A lobulated soft tissue mass (possibly nodal) in the mesenteric region encasing the superior mesenteric vessels and displacing bowel loops.
- Abdominal Organs: Liver, spleen, pancreas, bilateral kidneys, urinary bladder, and uterus were unremarkable.
- Impression: Mesenteric mass, likely nodal in origin, consistent with NHL.
What the March 2012 PET-CT Confirmed
A whole-body PET-CT scan conducted on 24-Mar-2012 (Report Approved: 28-Mar-2012) evaluated the response following surgery, radiotherapy, and 2 cycles of chemotherapy.
No Metabolically Active Residual or Recurrent Disease
- Primary Evaluation: No focal abnormal areas of increased tracer uptake were seen in the body.
- Impression: No metabolically active residual or recurrent disease.
Other Findings Identified
- Periportal Region: A subcentimeter lymph node was noted in the periportal region with mild tracer uptake, interpreted as inflammatory in nature (post-cholecystectomy).
- Lungs: A small cyst was noted in the right lung lower lobe.
- Surgical History: Evidence of prior cholecystectomy was noted.
What the April 2012 Brain & Spine MRI Showed
On 04-Apr-2012, an MRI scan of the brain and whole spine was performed due to complaints of generalized tonic-clonic seizures (GTCS) and backache:
- Brain: Cerebral parenchyma revealed a normal intensity pattern without focal or mass lesions, white matter changes, or abnormal meningeal enhancement. No evidence of brain metastasis.
- Spine: Residual mild marrow signal heterogeneity in vertebral bodies with marked regression compared to the baseline scan. Partial collapse of the D4 vertebra with subtle enhancing bilateral paravertebral thickening was noted. Spinal cord and cauda equina showed normal signal intensity with preserved disc heights.
What the July 2012 PET-CT Confirmed
A follow-up whole-body Time-of-Flight PET-CT scan was performed at Ganesh PET CT & Nuclear Medicine Centre on 03-Jul-2012.
Stable Low-Grade Mesenteric Lymph Nodes
- Abdominal Assessment: Examination revealed a few small mesenteric lymph nodes, the largest measuring 12 x 8 mm, exhibiting low-grade FDG uptake (Max SUV 4).
No Other Abnormal Focal Tracer Uptake
- Skeletal System: Non-FDG avid partial collapse of the D4 vertebra (consistent with previous MRI findings).
- Whole Body Survey: Neck, thorax, and pelvis revealed no abnormal FDG uptake. No other metabolically active focal uptake was identified across the body.
- Comparative Note: When compared to the previous PET-CT scan dated 28/03/2012, no significant time-interval changes were noted, confirming overall metabolic stability.
Blood & Pathology Profiles (May–June 2012)
Routine laboratory monitoring demonstrated stable hematological and biochemical parameters throughout the post-treatment phase:
| Parameter | 19/05/2012 Result | 21/06/2012 Result | Reference Range | Units |
| Hemoglobin | 11.9 | 13.5 | 11.5 – 16.0 | g/dL |
| Total Leucocyte Count (TLC) | 7,000 | 8,800 | 4,000 – 11,000 | /cmm |
| Platelet Count | 2.32 | 2.73 | 1.5 – 4.5 | Lakh/cmm |
| Serum Creatinine | 0.7 | 0.8 | 0.5 – 1.2 | mg/dL |
| SGOT (AST) | 39 | 45 | 4 – 37 | IU/L |
| SGPT (ALT) | 30 | 44 | 5 – 40 | IU/L |
| Blood Urea | — | 20 | 15 – 45 | mg/dL |
The Response Documented Over Time
| [Jan 2012] Uninvolved Bone Marrow & Mesenteric Mass Identified on MRI │ ▼ [Mar 2012] First PET-CT: Complete Absence of Metabolically Active Residual Disease │ ▼ [Apr 2012] Spine MRI: Marked Regression of Marrow Changes; No Brain Metastasis │ ▼ [Jul 2012] Follow-Up PET-CT: Sustained Stability; No New Focal Active Lesions |
What the Imaging and Pathology Reports Confirm
- Complete Metabolic Response: PET-CT imaging confirmed the clearance of hypermetabolic malignant lymphadenopathy and soft tissue masses.
- Bone Marrow Clearance: Biopsy results confirmed normal hematopoiesis without involvement by lymphoma cells.
- Sustained Remission: Sequential imaging across 2012 demonstrated long-term stability without evidence of active disease recurrence or new distant metastases.
Understanding the Diagnostic & PET-CT Findings
- FDG Uptake & SUV: Positron Emission Tomography measures glucose metabolism using Fluorodeoxyglucose (18F-FDG). Low-grade uptake (SUV ≤ 4) in residual subcentimeter nodes typically reflects post-inflammatory or reactive changes rather than active malignancy.
- Bone Marrow Uninvolvement: The absence of lymphoma cells in the bone marrow biopsy is an important favorable prognostic indicator in Non-Hodgkin’s Lymphoma / Anaplastic Large Cell Lymphoma management.
Conclusion
The clinical case of Mrs. Mansi Bhatia highlights a complete metabolic remission and sustained therapeutic stability in Anaplastic Large Cell Lymphoma / Non-Hodgkin’s Lymphoma. Comprehensive diagnostic tracking—from initial staging MRI and bone marrow biopsy to follow-up PET-CT scans—documented the complete resolution of active disease and normal lab recovery.
Every Lymphoma Case Requires Individual Assessment
Disclaimer: Every oncology case presents unique clinical variables. Treatment options, diagnostic monitoring protocols, and outcomes vary based on individual staging, histological sub-types, and patient-specific factors. Consultation with a qualified oncologist is essential for personalized medical evaluation.
Medical Reports
(Diagnostic PET-CT scans, MRI reviews, Bone Marrow Pathology, and Clinical Biochemistry reports from Rajiv Gandhi Cancer Institute & Research Centre and Ganesh PET CT Centre)
Medical Reports
Frequently Asked Questions
It indicates that the tumor mass or affected lymph nodes no longer consume abnormal amounts of radioactive sugar tracer (18F-FDG), confirming that active cancer cells are no longer detectable at the scanned sites.
A bone marrow biopsy determines whether the lymphoma has spread into the blood-forming tissue, which helps dictate accurate staging and therapeutic planning.
Low-grade uptake (SUV < 4) often represents benign, inflammatory, or post-treatment healing tissues rather than persistent active lymphoma.