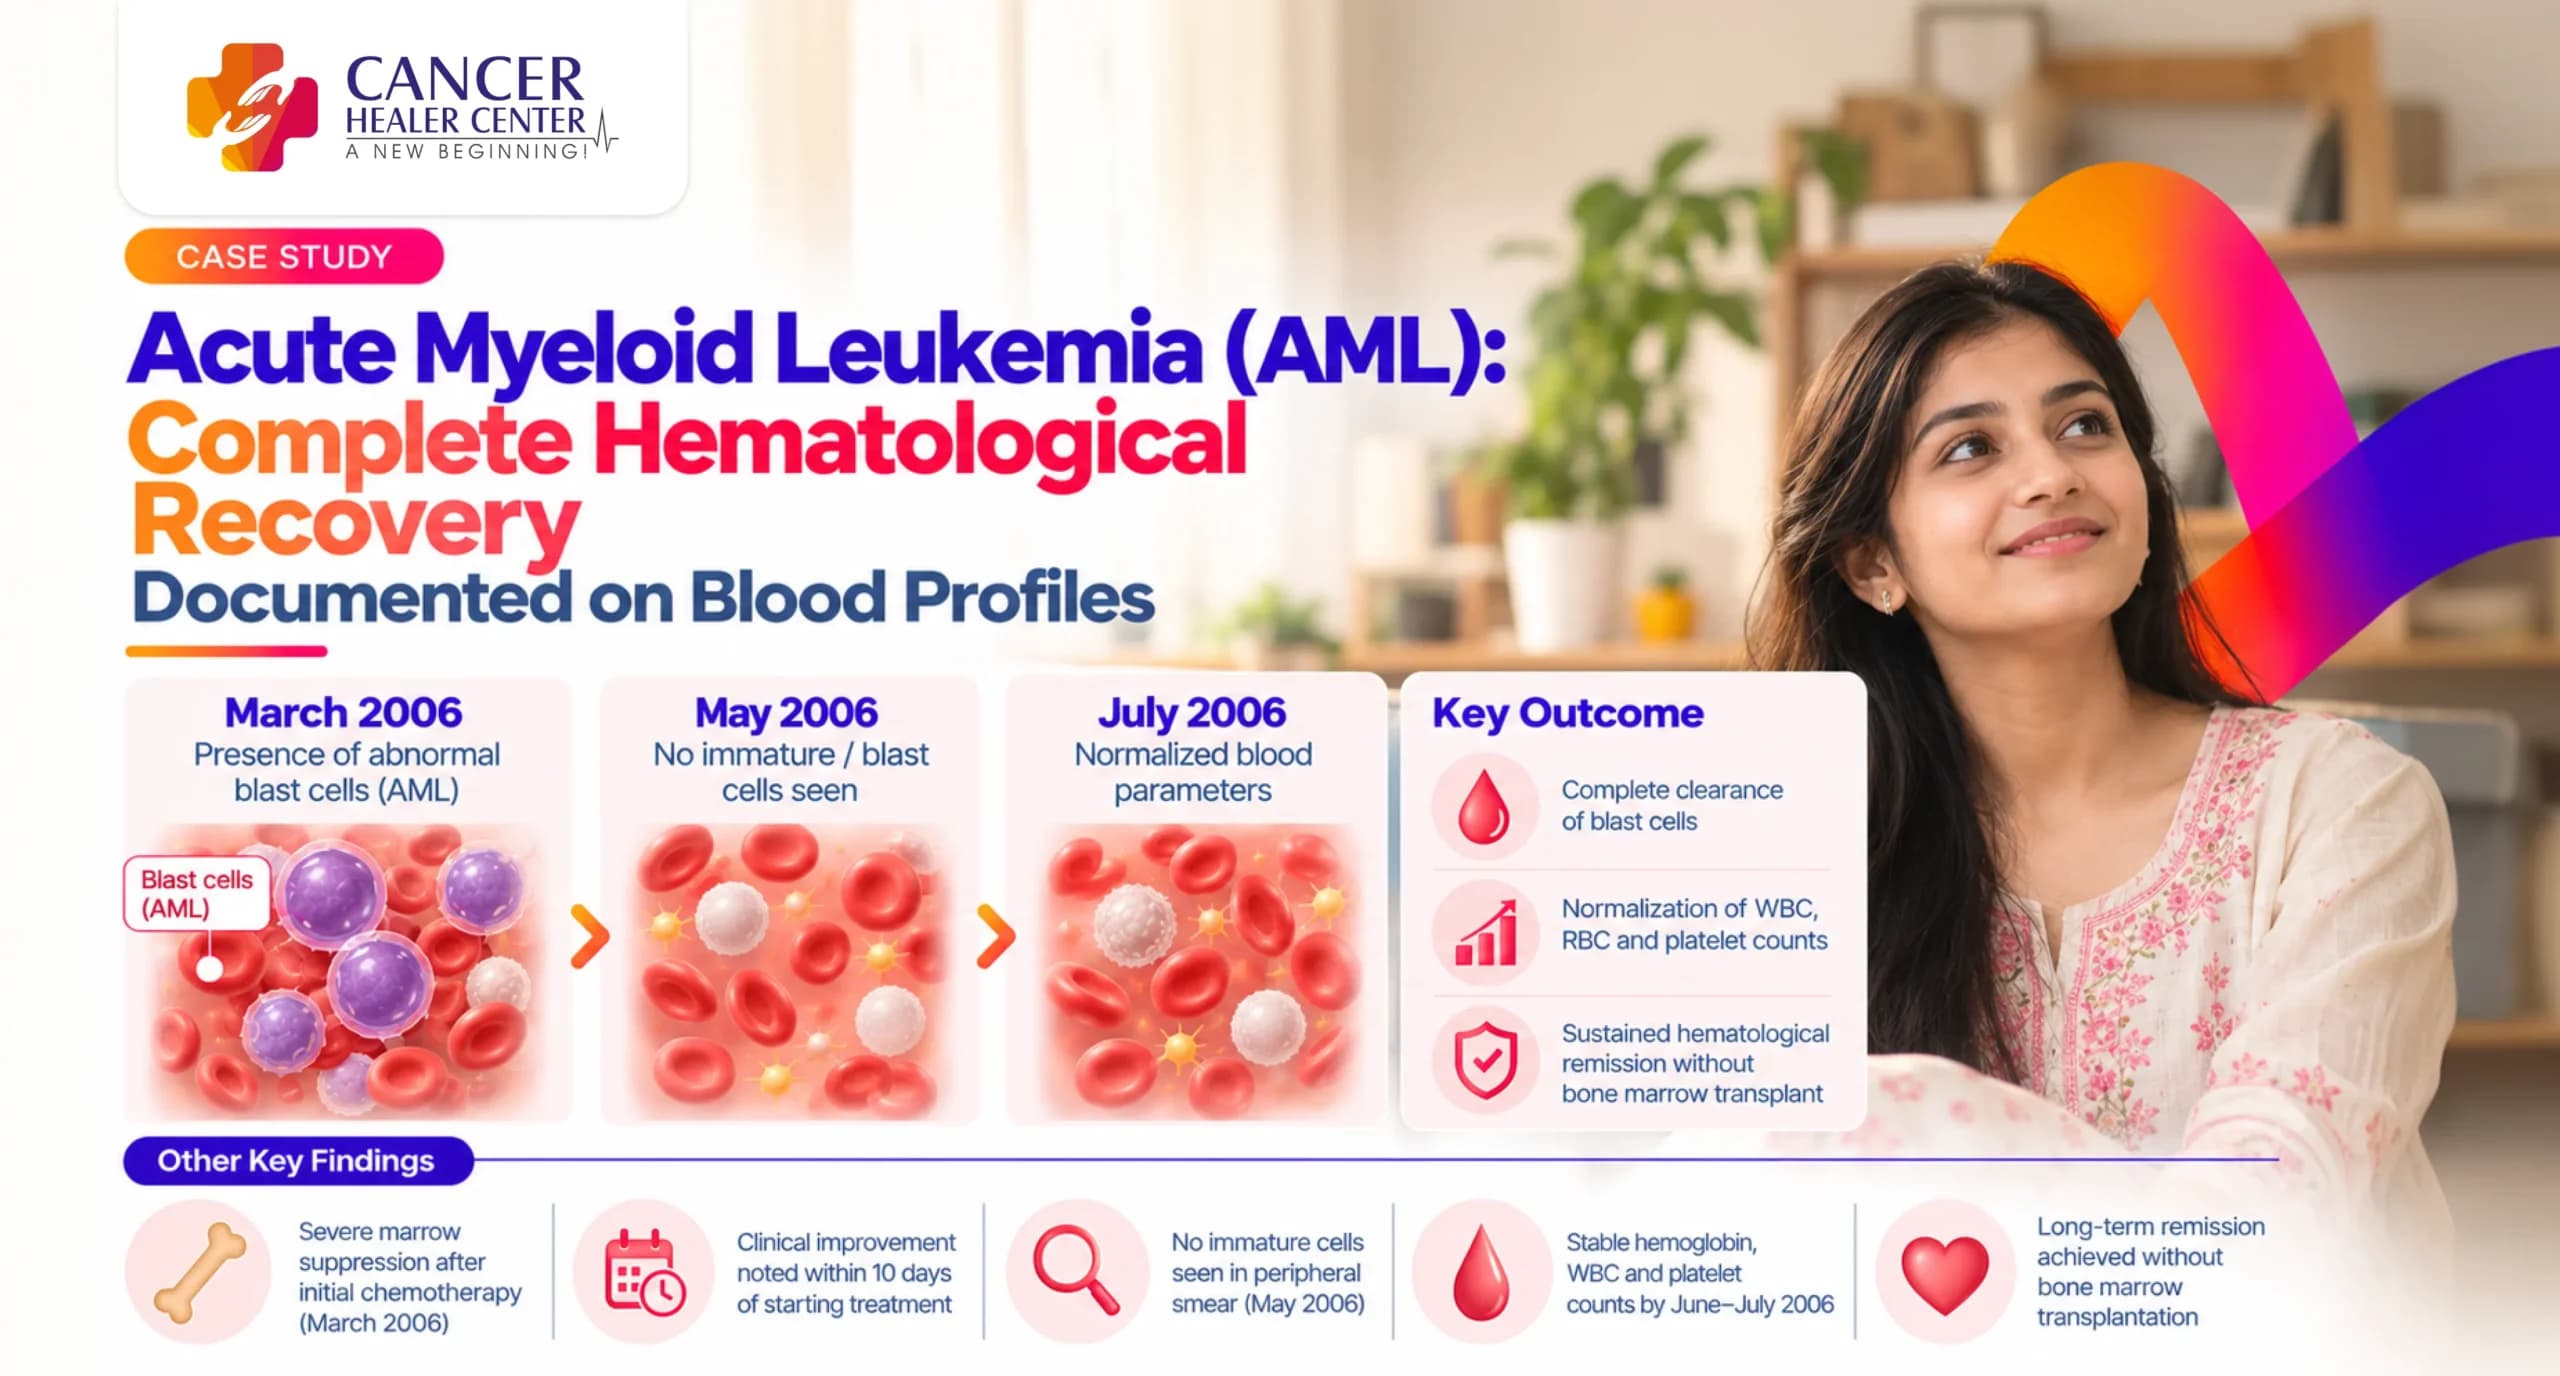
A Strong Response Documented Across Serial Hematology Scans
This case study documents the clinical progress, systemic recovery, and sustained hematological remission of an 18-year-old female diagnosed with Acute Myeloid Leukemia (AML). Serial evaluation through complete hemogram panels and peripheral blood smear examinations from March 2006 to July 2006 demonstrated progressive recovery of red cell mass, normalization of white blood cell counts, complete clearance of circulating blast cells, and restoration of stable platelet levels without requiring bone marrow transplantation.
Neha Barua’s Case at a Glance
| Patient Name: | Ms. Neha Barua |
| Age / Gender: | 18–19 Years / Female |
| Referred By: | Dr. Sahu MD / Dr. R. Pathak MD |
| Primary Diagnosis: | Acute Myeloid Leukemia (AML) / Blood Cancer |
| Clinical Presentation: | Severe acute bone marrow suppression, poor vital prognosis following primary chemotherapy cycle at Jawaharlal Nehru Hospital, Bhopal, and recommendation for Bone Marrow Transplantation (BMT) |
| Treatment Phase: | Integrated Cancer Healer Therapy (Immunotherapy) / Supportive Care |
| Primary Outcome: | Rapid clinical improvement within 10 days, complete clearance of immature/blast cells, normalization of all CBC parameters over 6 months, and long-term remission without BMT |
Neha Barua’s Treatment Journey
Ms. Neha Barua presented in early 2006 with Acute Myeloid Leukemia (AML). Following an initial cycle of chemotherapy at Jawaharlal Nehru Hospital in Bhopal, her clinical prognosis was extremely critical, and she was referred to Mumbai for a Bone Marrow Transplant. In March 2006, prior to BMT, her family initiated Cancer Healer therapy (immunotherapy) under Dr. Hari Krishna and Dr. Tarang Krishna. Clinical improvement was noted within 10 days of starting treatment. Sequential laboratory tracking via Dr. Maity’s Bhopal Pathlabs and Kothari Diagnostic Centre documented step-by-step restoration of healthy hematopoiesis, allowing the patient to achieve full recovery without undergoing bone marrow transplantation.
What the Initial Diagnostic Workup Showed (March 2006)
Initial Hemogram and Peripheral Smear Findings
A Complete Hemogram conducted at Dr. Maity’s Bhopal Pathlabs & Diagnostic Centre on 05-Mar-2006 (Lab No: R-186) demonstrated baseline hematological parameters following primary induction chemotherapy:
- Hemoglobin: 11.9 g/dL (Reference Range: 11.5 – 16.0 g/dL)
- Total WBC Count: 5,000 /cmm (Reference Range: 4,000 – 11,000 /cmm)
- Differential Leucocyte Count: Neutrophils 41%, Lymphocytes 47%, Monocytes 3%, Eosinophils 9%, Basophils 0%
- Platelet Count: 2.23 Lakhs/cmm (Reference Range: 1.5 – 4.5 Lakhs/cmm)
- Erythrocyte Sedimentation Rate (ESR): 19 mm/hr
Prognostic Assessment at Presentation
- Clinical Status: Severe post-chemotherapy marrow compromise and critical vital prognosis.
- Surgical Recommendation: Bone Marrow Transplantation advised due to high risk of rapid disease relapse.
What the April 2006 Hemogram Confirmed
A follow-up Complete Blood Count (C.B.C.) was performed at Dr. Maity’s Bhopal Pathlabs on 09-Apr-2006 (Lab No: R-409).
Hemoglobin and RBC Count Recovery
- Hemoglobin Level: Increased to 12.4 g/dL.
- RBC Count: 4.23 million/cmm with Packed Cell Volume (PCV) of 39.8%.
Differential Leucocyte Count Stabilization
- Total Leucocyte Count: 5,900 /cmm.
- Differential Distribution: Neutrophils 48%, Lymphocytes 41%, Monocytes 2%, Eosinophils 9%.
- Platelet Count: Maintained stably at 2.50 Lakhs/cmm.
- ESR: Reduced to 10 mm/hr.
What the May 2006 Hemogram Confirmed
On 03-May-2006, follow-up pathology evaluation (Lab No: SP-26) provided critical evidence regarding circulating disease status.
Complete Absence of Blast Cells
- Pathology Remark: “No immature cells (Blast Cells) seen.”
- Differential Count: Neutrophils 65%, Lymphocytes 26%, Monocytes 2%, Eosinophils 7%.
Normocellular Leucocyte & Platelet Response
- Total Leucocyte Count: Normal rise to 7,200 /cmm.
- Hemoglobin: Stable at 12.6 g/dL.
- Platelet Count: 2.40 Lakhs/cmm.
What the June & July 2006 Hemograms Showed
Sustained Hematological Remission in June 2006
A detailed C.B.C. and peripheral smear evaluation conducted on 04-Jun-2006 (Lab No: R-132) confirmed ongoing stability:
- Hemoglobin: Rose to 14.4 g/dL.
- Total WBC Count: 8,200 /cmm.
- Differential Count: Neutrophils 69%, Lymphocytes 24%, Monocytes 2%, Eosinophils 5%.
- Platelet Count: 2.90 Lakhs/cmm.
- Peripheral Smear Remarks: Mild anisochromic & anisocytic smear; “No immature WBCs seen. No Blast cells seen.” Hemoparasites absent.
Normal Blood Profile Confirmed in July 2006
Comprehensive blood examination at Kothari Diagnostic Centre on 08-Jul-2006 (Ref No: 60) confirmed full hematological normalization:
- Hemoglobin: 13.6 g/dL.
- Total Leucocyte Count: 9,800 /cmm (Polymorphs 68%, Lymphocytes 26%, Monocytes 2%, Eosinophils 4%).
- Platelet Count: 2.57 Lakhs/cmm.
- PCV: 42.5%.
Complete Blood Count (CBC) Profiles Over Time
The table below summarizes the sequential restoration of peripheral blood parameters across the 5-month monitoring period:
| Parameter | 05/03/2006 | 09/04/2006 | 03/05/2006 | 04/06/2006 | 08/07/2006 | Reference Range | Units |
| Hemoglobin | 11.9 | 12.4 | 12.6 | 14.4 | 13.6 | 11.5 – 16.0 | g/dL |
| RBC Count | 4.17 | 4.23 | 4.82 | 5.26 | 4.62 | 4.0 – 5.6 | mill/cmm |
| Total WBC Count | 5,000 | 5,900 | 7,200 | 8,200 | 9,800 | 4,000 – 11,000 | /cmm |
| Neutrophils | 41 | 48 | 65 | 69 | 68 | 40 – 75 | % |
| Lymphocytes | 47 | 41 | 26 | 24 | 26 | 20 – 45 | % |
| Platelet Count | 2.23 | 2.50 | 2.40 | 2.90 | 2.57 | 1.5 – 4.5 | Lakhs/cmm |
| Blast Cells | — | — | Absent | Absent | Absent | 0 | % |
The Response Documented Over Time
| [March 2006] Post-Chemotherapy Evaluation; High-Risk AML & BMT Advised │ ▼ [April 2006] Initiation of Cancer Healer Therapy; WBC & RBC Levels Begin Recovery │ ▼ [May 2006] Peripheral Smear Confirms Complete Absence of Blast Cells (Immature WBCs) │ ▼ [June–July 2006] Complete Normalization of Hemoglobin (13.6–14.4 g/dL), Platelets, & Total WBCs |
What the Pathology Reports Confirm
- Complete Clearance of Leukemic Blasts: Repeated peripheral smear checks confirmed the complete absence of circulating immature leukemic blast cells.
- Restoration of Healthy Bone Marrow Function: Continuous elevation and stabilization of absolute neutrophil and platelet counts without persistent cytopenias.
- Long-Term Remission Without BMT: Full systemic recovery achieved through oral therapy, avoiding aggressive bone marrow transplantation procedures.
Understanding the Hematological Findings
- Absence of Blast Cells: Leukemic blast cells are immature white blood cells that overproduce in acute myeloid leukemia, crowding out normal blood components. Complete absence of blasts in peripheral smears signifies complete disease remission.
- Normalization of Differential Counts: Restoration of a healthy ratio between neutrophils and lymphocytes indicates the recovery of adaptive and innate immune functionality.
Conclusion
The clinical case of Ms. Neera Barua highlights a complete hematological remission in Acute Myeloid Leukemia (AML). Sequential laboratory testing over five months documented the complete clearance of circulating blast cells, steady restoration of red blood cell and platelet counts, and long-term functional recovery.
Every Acute Myeloid Leukemia Case Requires Individual Assessment
Disclaimer: Case outcomes in acute myeloid leukemia depend on specific cytogenetic mutations, baseline blast percentages, age, and individual response to systemic immunotherapies. Clinical protocols and monitoring must be directed by a qualified hematologist or oncologist.
Medical Reports
(Diagnostic hematology and blood pathology reports from Dr. Maity’s Bhopal Pathlabs & Diagnostic Centre and Kothari Diagnostic Centre, alongside handwritten patient testimonial correspondence)
Medical Reports
Frequently Asked Questions
It indicates that abnormal, immature leukemic cells are no longer circulating in the bloodstream, serving as a primary marker of complete hematological remission.
Serial blood profiles allow doctors to track the recovery of healthy blood cell production (red cells, white cells, platelets) and rapidly detect any early recurrence of abnormal cells.
When patient blood counts normalize fully and blast cells are cleared through effective systemic therapy, bone marrow transplantation may not be required, provided long-term remission is maintained.