

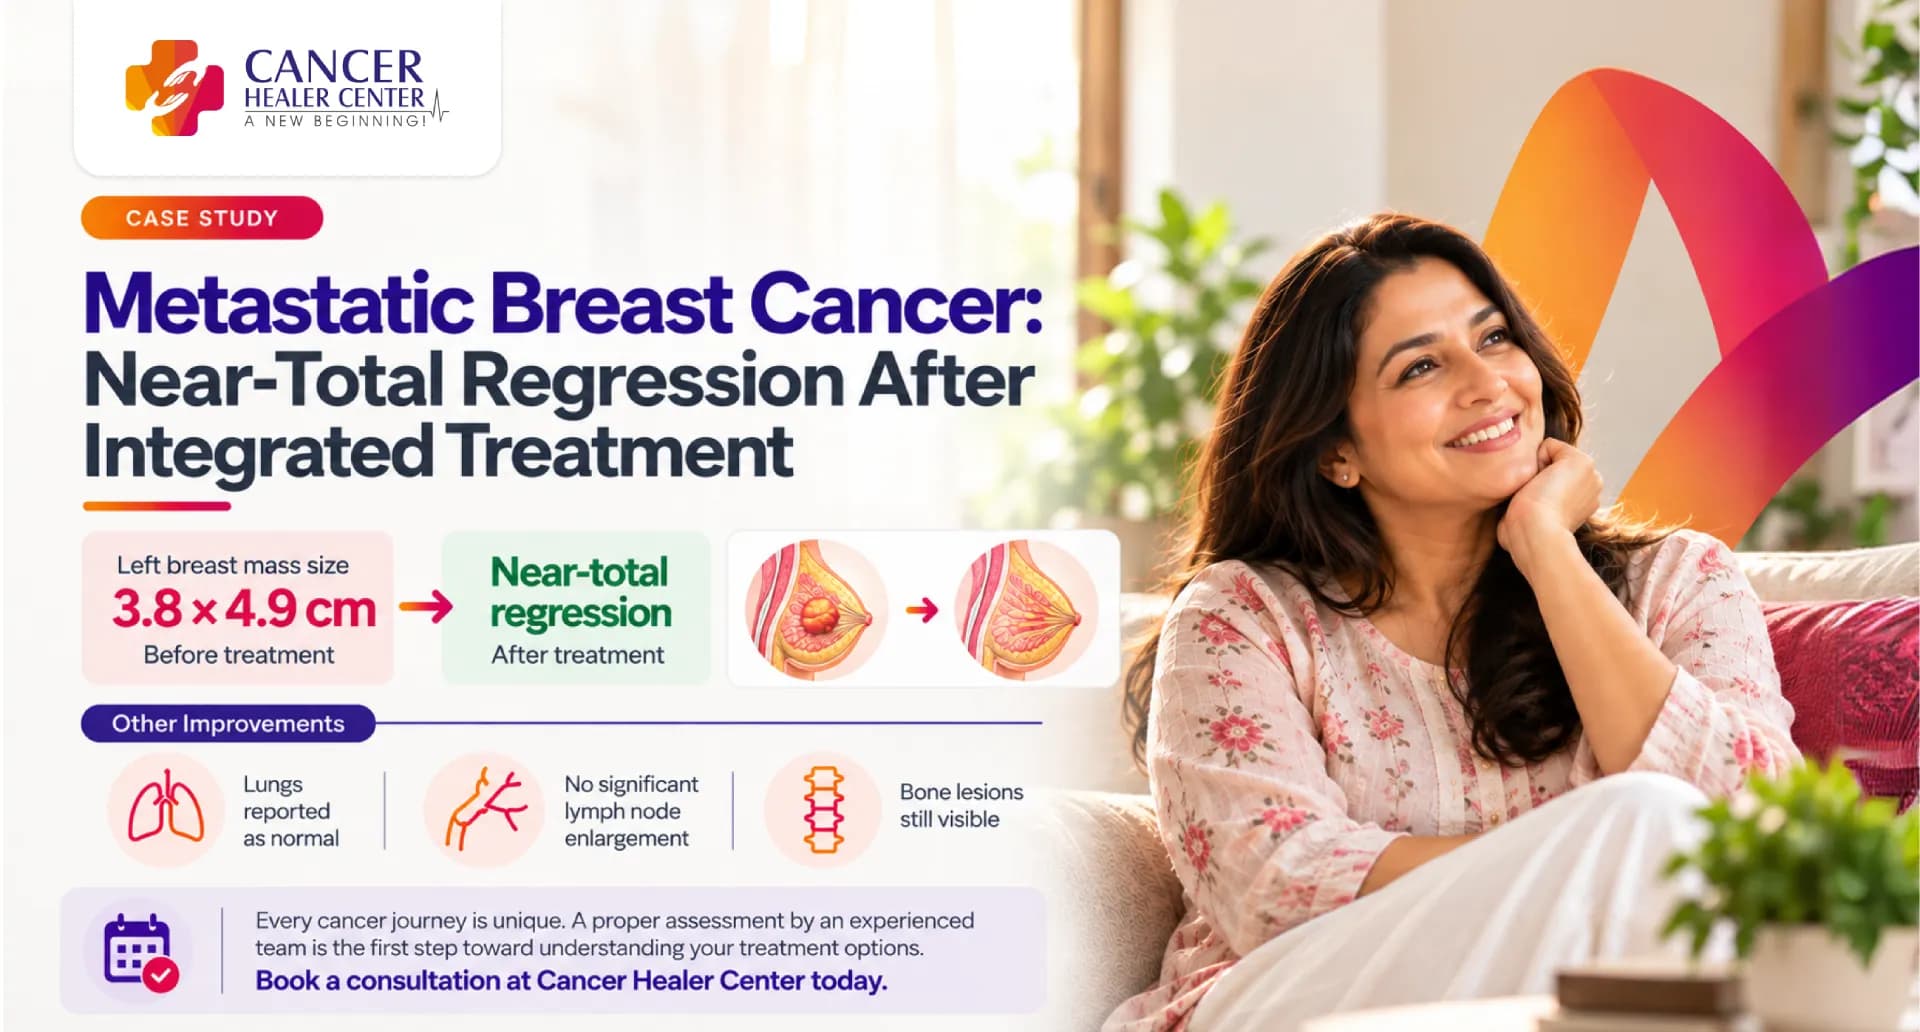
From Extensive Disease to a Major Radiological Response
Mrs Poonam was approximately 30 years old when she was being treated for invasive ductal carcinoma of the left breast. She had undergone a lumpectomy in January 2009. By February 2010, imaging showed a 3.8 × 4.9 cm mass in the left breast, left axillary lymph nodes, small nodular lesions in both upper lung lobes and multiple bone lesions. A separate abdominal CT also identified a small liver lesion and a few left para-aortic lymph nodes.
According to her family, Mrs Poonam received treatment from Dr Tarang Krishna for approximately two months. Her hospital records mention Ayurvedic or alternative treatment and also refer to three treatment cycles completed by 26 March 2010. The available reports do not specify what these three cycles involved.
When Mrs Poonam underwent repeat imaging at Rajiv Gandhi Cancer Institute and Research Centre on 16 April 2010, the CT showed near-total regression of the left breast mass and complete regression of the liver lesion. Both lungs were reported as normal, and no significant mediastinal or retroperitoneal lymphadenopathy was seen. Lytic and sclerotic bone lesions remained visible in the spine, sacrum and both iliac bones.
Note: This case study presents Mrs Poonam’s documented experience and radiological response during her care journey. Individual outcomes may vary depending on the type and stage of cancer, overall health and response to treatment.
Mrs Poonam’s Case at a Glance
| Patient detail | Documented information |
| Patient | Mrs Poonam |
| Age | 30 years in the first report and 31 years in the subsequent hospital reports |
| Diagnosis | Invasive ductal carcinoma of the left breast |
| Previous surgery | Lumpectomy in January 2009 |
| Baseline scans | 2 and 5 February 2010 |
| Treatment information | Approximately two months of treatment from Dr Tarang Krishna, according to the family; the hospital records also mention Ayurvedic or alternative treatment and three treatment cycles |
| Follow-up CT | 16 April 2010 |
| Key outcome | Near-total regression of the left breast mass and complete regression of the liver lesion |
| Other follow-up findings | Both lungs were reported as normal, with no significant mediastinal or retroperitoneal lymphadenopathy |
| Finding still visible | Lytic and sclerotic lesions in the dorsolumbar vertebrae, sacrum and both iliac bones |
Mrs Poonam’s Cancer Journey
Mrs Poonam underwent a lumpectomy for cancer of the left breast in January 2009. The clinical history recorded in her hospital report states that histopathological examination showed invasive ductal carcinoma.
By February 2010, she had presented again with a mass in the left breast and findings indicating disease beyond the primary breast tumour. Her chest CT showed left axillary lymph nodes, small nodular densities in both upper lung lobes and multiple lytic lesions in the dorsal vertebrae. The radiologist specifically described the vertebral findings as metastases.
A CT of the abdomen performed three days later showed a small lesion in the right lobe of the liver, a few left para-aortic lymph nodes and multiple lytic lesions involving the dorsolumbar vertebrae, sacrum and both iliac bones.
Mrs Poonam’s family described her condition as stage IV breast cancer. The hospital reports separately documented a left breast mass with metastatic disease. Her family approached Dr Tarang Krishna, and she received treatment from him for approximately two months before returning to Rajiv Gandhi Cancer Institute and Research Centre for response assessment.
What the February 2010 Scans Showed
Chest CT: 2 February 2010
A contrast-enhanced CT of the chest performed at Jindal Institute of Medical Sciences documented the following findings:
| Area assessed | Finding |
| Left breast | Heterogeneous mass measuring 3.8 × 4.9 cm |
| Posterior extent | Mass reached the pectoralis muscle |
| Skin and subcutaneous tissue | Inhomogeneous stranding in the subcutaneous fat with thickening of the overlying skin |
| Left axilla | Lymph nodes were present; the largest measured 1.5 × 1.7 cm |
| Lungs | Small nodular densities in both upper lobes |
| Bones | Multiple lytic lesions in the dorsal vertebrae |
| Trachea and main bronchi | Normal |
| Heart and great vessels | Normally opacified |
| Oesophagus | Collapsed and appeared normal |
| Pleura and pericardium | No evidence of pleural or pericardial effusion |
| Other visualised organs | Liver, gallbladder, spleen, pancreas and kidneys appeared normal within the visualised area |
The radiologist’s impression was suggestive of:
- A mass in the left breast with axillary lymph nodes
- Nodular lesions in both upper lung lobes
- Dorsal vertebral metastases
Clinicopathological correlation was advised.
Abdominal CT: 5 February 2010
A CT of the whole abdomen performed at Rajiv Gandhi Cancer Institute and Research Centre reported:
| Area assessed | Finding |
| Liver | Small peripheral, ill-defined hypodense lesion in the right lobe |
| Biliary system | No intrahepatic biliary dilatation |
| Para-aortic region | A few subcentimetre left para-aortic lymph nodes |
| Bones | Multiple lytic lesions in the dorsolumbar vertebrae, sacrum and both iliac bones |
| Left adnexa | Simple cyst measuring 5.4 × 3.6 cm |
| Ascites | Not seen |
| Other abdominal organs | Gallbladder, spleen, pancreas, adrenals and both kidneys appeared normal |
| Urinary bladder | Normal |
| Uterus | Normal, with an IUCD in situ |
The clinical history included in this report recorded a previous lumpectomy, invasive ductal carcinoma and presentation with a left breast mass with metastatic disease.
Treatment Before the Follow-Up Scan
According to the handwritten statement provided by her family, Mrs Poonam received treatment from Dr Tarang Krishna for approximately two months. Her family reported considerable relief during this period and later returned to Rajiv Gandhi Cancer Institute and Research Centre for another assessment.
The February hospital record states that she had taken Ayurvedic treatment. The April record refers to alternative treatment and also states that she was assessed after three treatment cycles completed by 26 March 2010.
The available records do not identify what the three treatment cycles involved. They also do not include the names, doses or duration of the medicines given during this period.
The documented information establishes the sequence of care and the changes seen on follow-up imaging. It does not provide enough detail to assess the separate contribution of each component of treatment.
What Changed on the Follow-Up CT
On 16 April 2010, Mrs Poonam underwent a contrast-enhanced CT of the chest and whole abdomen at Rajiv Gandhi Cancer Institute and Research Centre. The scan was performed to evaluate her response to treatment.
The Breast Mass Showed Near-Total Regression
The February CT had shown a 3.8 × 4.9 cm mass in the left breast reaching posteriorly to the pectoralis muscle.
On the April CT, the radiologist described mild soft-tissue thickening in the parasternal region and overlying skin. The formal comparison concluded that the left breast mass had shown near-total regression.
The Liver Lesion Showed Complete Regression
The February abdominal CT had identified a small, peripheral, ill-defined hypodense lesion in the right lobe of the liver.
On the follow-up scan, the liver appeared normal, with no focal lesion or dilated intrahepatic biliary channels. The radiologist concluded that the liver lesion had shown complete regression.
Both Lungs Were Reported as Normal
Small nodular densities had been seen in both upper lung lobes on the February chest CT.
On the April scan, both lungs were reported as normal. The trachea, main bronchi and major mediastinal vessels were also normal. No significant mediastinal lymphadenopathy or pleural or pericardial effusion was identified.
The follow-up report did not separately measure or characterise the previously described lung nodules. It is therefore most accurate to state that both lungs were reported as normal on the later scan.
No Significant Retroperitoneal Lymphadenopathy Was Seen
A few subcentimetre left para-aortic lymph nodes had been reported on the February abdominal scan.
The April CT found no significant retroperitoneal lymphadenopathy. No ascites was seen.
Bone Lesions Remained Visible
The initial scans showed multiple lytic lesions in the dorsal and dorsolumbar vertebrae, sacrum and both iliac bones.
The April CT continued to show lytic and sclerotic lesions in the dorsolumbar vertebrae, sacrum and both iliac bones. The report did not clarify whether the sclerotic changes represented treated disease, healing changes or another process. The most accurate interpretation is that bone lesions remained visible on the follow-up CT.
The Change Documented Across the Two Assessments
| Finding | February 2010 | 16 April 2010 | Documented outcome |
| Left breast mass | 3.8 × 4.9 cm mass reaching the pectoralis muscle | Mild soft-tissue thickening in the parasternal region and overlying skin | Near-total regression |
| Liver lesion | Small hypodense lesion in the right hepatic lobe | No focal liver lesion | Complete regression |
| Lung findings | Small nodular densities in both upper lobes | Both lungs were reported as normal | Previously described nodules were not separately discussed |
| Mediastinal lymph nodes | No significant enlargement documented | No significant mediastinal lymphadenopathy | No significant lymphadenopathy |
| Para-aortic lymph nodes | A few subcentimetre left para-aortic lymph nodes | No significant retroperitoneal lymphadenopathy | No significant lymphadenopathy |
| Bone lesions | Multiple lytic lesions in the vertebrae, sacrum and iliac bones | Lytic and sclerotic lesions remained visible | Bone lesions remained visible on CT |
| Pleural or pericardial effusion | Not seen | Not seen | No effusion |
| Ascites | Not seen | Not seen | No ascites |
How Her Family Described the Experience
Mrs Poonam’s family wrote that she was approximately 30 years old and had stage IV breast cancer. They stated that after receiving treatment from Dr Tarang Krishna for around two months, they returned to Rajiv Gandhi Cancer Institute and Research Centre in Delhi for another check-up.
According to the family, the follow-up reports showed substantial improvement. They expressed gratitude for the relief Mrs Poonam experienced during treatment and referred to complete regression in their written account.
The formal radiology report provides a more specific description of the response. It records near-total regression of the left breast mass and complete regression of the liver lesion, while bone lesions remained visible.
What the Medical Reports Confirm
The follow-up assessment provides objective radiological evidence of a major response over approximately ten weeks. The principal documented findings were:
- Near-total regression of the left breast mass
- Complete regression of the liver lesion
- Normal appearance of both lungs on follow-up imaging
- No significant mediastinal lymphadenopathy
- No significant retroperitoneal lymphadenopathy
- No pleural or pericardial effusion
- No ascites
Lytic and sclerotic bone lesions remained visible in the dorsolumbar vertebrae, sacrum and both iliac bones. The case should therefore not be described as complete regression or disappearance of all documented disease.
The records document the radiological response during Mrs Poonam’s treatment journey. As the complete treatment details are not included in the supplied reports, the findings are presented as recorded without assigning the response to an individual component of care.
Conclusion
Mrs Poonam’s case documents a major radiological response during treatment for invasive ductal carcinoma of the left breast with metastatic disease.
In February 2010, imaging showed a 3.8 × 4.9 cm left breast mass, left axillary lymph nodes, nodular abnormalities in both upper lung lobes, a liver lesion and multiple bone lesions. By 16 April 2010, the breast mass had shown near-total regression, while the liver lesion had shown complete regression. Both lungs were reported as normal, and no significant mediastinal or retroperitoneal lymphadenopathy was seen.
Lytic and sclerotic bone lesions remained visible in the dorsolumbar vertebrae, sacrum and both iliac bones, supporting the need for continued medical assessment and monitoring.
This case presents one patient’s documented experience and radiological response. Outcomes may differ according to the type and stage of cancer, previous treatment, overall health and individual response to care.
Every Cancer Journey Needs an Individual Review
If you or a family member is living with advanced breast cancer, the team at Cancer Healer Center can review your medical reports, previous treatment and present health needs to discuss an individualised care approach.





Frequently Asked Questions
The clinical history recorded in the hospital report states that histopathological examination showed invasive ductal carcinoma of the left breast.
The hospital’s clinical history described a left breast mass with metastatic disease. The chest CT also specifically reported dorsal vertebral metastases. Additional abnormalities were documented in the lungs, liver, abdominal lymph nodes and other bones.
The chest CT performed on 2 February 2010 measured the left breast mass at 3.8 × 4.9 cm.
The follow-up CT documented near-total regression of the left breast mass and complete regression of the liver lesion. Both lungs were reported as normal, and there was no significant mediastinal or retroperitoneal lymphadenopathy.
The reports do not document the disappearance of all disease. Lytic and sclerotic lesions remained visible in the dorsolumbar vertebrae, sacrum and both iliac bones.
The initial scans were performed on 2 and 5 February 2010. The follow-up CT was performed on 16 April 2010, approximately ten weeks later.
The family states that Mrs Poonam received treatment from Dr Tarang Krishna for approximately two months. The medical records mention Ayurvedic or alternative treatment and three treatment cycles completed by 26 March 2010. The reports do not provide the names or details of the treatments involved.
Cancer response differs from one patient to another. It may be influenced by the cancer type, stage, previous treatment, overall health and individual response to care. This case documents Mrs Poonam’s experience and does not guarantee the same outcome for another patient.

